
Webster Technique Prenatal Authority: The Clinical Guide to Pelvic Balance and Sacral Alignment in Huntington Beach
The Webster Technique is a specific chiropractic assessment and adjustment protocol used to evaluate and correct sacral and pelvic misalignment during pregnancy. It is performed only by chiropractors who hold advanced certification in the method, because the protocol requires specialized training beyond a general chiropractic license. The technique centers on the sacrum and its supporting ligaments and muscles. It analyzes whether the pelvis is carrying the mechanical load of pregnancy evenly or concentrating that stress in ways that create tension and restriction. When pelvic balance is compromised, the resulting misalignment can contribute to a condition called intrauterine constraint, a mechanical limit on the space available inside the uterus during later gestation. A certified adjustment addresses the joint dysfunction and soft tissue tension believed to underlie that constraint, using a diversified adjustment approach rather than a generic spinal correction. The goal is to enhance neuro-biomechanical function in the pelvis. It is not a method for manually repositioning a baby. Any effect on fetal position is considered a secondary result of improved pelvic balance and reduced ligament tension, not the direct mechanism of the adjustment itself. The protocol is applied throughout pregnancy as part of ongoing prenatal chiropractic care, with the analysis and adjustment adapted to the specific biomechanical findings present at each visit. Because the technique targets a precise structural relationship between the sacrum, the pelvis, and the ligaments supporting the uterus, its clinical value depends directly on the practitioner's certification and training in this exact protocol, which distinguishes it from a standard adjustment applied to a pregnant patient without that specialized analysis.
Last Updated: 2026-09-15
Articles in this cluster
- Sacral Subluxation and How Does — What Is Sacral Subluxation and How Does Pelvic Misalignment Impact Pregnancy Comfort?
- Relieving Pregnancy Sciatica in Huntington — Relieving Pregnancy Sciatica in Huntington Beach: Why Standard Stretches Aren't Clearing the Nerve Pressure
- Webster Technique vs. Standard Care — Webster Technique vs. Standard Care for Pregnancy Pelvic Girdle Pain
- Biomechanics of Round Ligament Tension: — The Biomechanics of Round Ligament Tension: How Webster Technique Restores Pelvic Symmetry
- Pelvic Constraint and Fetal Positioning: — Pelvic Constraint and Fetal Positioning: The Clinical Role of the Webster Technique
- Chiropractic Adjustment Safe During the — Is Chiropractic Adjustment Safe During the Third Trimester? What the Clinical Evidence Shows
- Inside Dr. Aimee's Webster Technique — Inside Dr. Aimee's Webster Technique Protocol: What to Expect During Your Prenatal Assessment in Huntington Beach
- Prenatal Yoga and Home Exercises — Why Prenatal Yoga and Home Exercises Can't Fix a Structurally Misaligned Sacrum
- Webster-Certified vs. General Chiropractor: Why — Webster-Certified vs. General Chiropractor: Why Specialization Matters for Prenatal Care
- Resolving Pubic Symphysis Dysfunction with — Resolving Pubic Symphysis Dysfunction with Webster-Certified Prenatal Chiropractic Care
- Second and Third Trimester Postural — How Second and Third Trimester Postural Shifts Alter Your Pelvic Ring: A Biomechanical Breakdown
What the Webster Technique Actually Is (and Isn't)
The Webster Technique is a defined protocol. It is not a loose label for adjusting a pregnant patient. It names one assessment sequence and one correction, both built around the pelvis as the foundation carrying the weight of pregnancy.
That foundation does one of two things. It spreads the load evenly across the pelvis, or it piles it onto one side. The whole point of the protocol is to tell a practitioner which one is happening before a single adjustment is made.
Most of the confusion comes from what the name sounds like it should do. It sounds like a move aimed at the baby. It is not.
It is a structural correction aimed at the pelvis. Anyone looking at prenatal chiropractic care for a shifting pregnancy should understand that difference first, before anything else.
The ICPA's Working Definition
The International Chiropractic Pediatric Association spells the terms out precisely. The Webster Technique is a specific assessment and diversified adjustment, applied to any weight-bearing individual, built to enhance neuro-biomechanics in that person.
That definition matters because it is deliberately narrow. It describes an assessment paired with an adjustment, not a broad category of prenatal bodywork, and the framework behind that definition is documented in published positional statements covering credentialed chiropractic practice.
What the Technique Does Not Claim to Do
What the technique does not claim matters just as much as what it does. It does not claim to physically turn a baby.
The Webster Technique is a specific chiropractic analysis and adjustment focused on pelvic balance. It is not a method for manually turning babies. Correcting the foundation is the whole task, and any change in the baby's position that follows is a consequence, never the mechanism.
Why 'Any Chiropractor Can Adjust a Pregnant Patient' Is a Dangerous Assumption
Here's the part that gets skipped. A chiropractic license does not include prenatal specialization. That credential covers general adjustment, not the sacral analysis the Webster Technique is built on.
Webster Certification through the International Chiropractic Pediatric Association is the credential that actually establishes prenatal competency. Most practitioners adjusting pregnant patients do not hold it, so the foundation never gets assessed. And a small maternal pelvis is already recognized as one of the mechanical factors that can constrain fetal position in later gestation, alongside uterine malformation and aberrant positioning that PMC-indexed research has documented.
That is precisely the mechanical territory a generic adjustment is not built to evaluate. Load gets distributed. Nobody checked whether it was distributed evenly.
Why the Generic Adjustment Model Fails Pregnant Patients

A chiropractic license lets a doctor adjust a spine. It does not certify that same doctor to read the pregnant pelvis as a load-bearing structure.
And that gap almost never gets said out loud. Most patients walk in assuming any adjustment offered during pregnancy has already accounted for what pregnancy does to the body.
The market runs on that same assumption. A general adjustment gets scheduled, performed, and billed the same way whether the doctor has prenatal-specific training or none at all.
Nothing about that transaction verifies whether the sacrum was actually assessed. The foundation either got evaluated for uneven load, or it did not, and the appointment looks identical either way.
The Failure Mechanism Behind Unspecialized Prenatal Care
A standard adjustment corrects segmental joint restriction. It was never built to isolate the sacral and ligamentous findings that come with a shifting pelvic foundation under pregnancy load.
Skip that isolation, and an adjustment can quiet a symptom while the real pelvic imbalance sits untouched. The mechanism piling stress onto one side of the pelvis keeps right on working.
This is where the assumption that any licensed doctor can competently adjust a pregnant patient falls apart. Competency to adjust a spine is not competency to analyze a pregnant pelvis, yet the two get treated as the same thing.
What Gets Missed Without a Pelvic-Specific Protocol
A pelvic-specific protocol follows how load moves through the sacrum, the supporting ligaments, and the muscle around them across the whole pregnancy. A generic adjustment follows none of it. It handles whatever joint reads as restricted that day.
The uneven load this section keeps returning to does not resolve on its own. Achieving neuro-biomechanical balance in the pelvis is what makes the rest of pregnancy more comfortable and supports a smoother labor and delivery, and that balance is exactly what an unspecialized adjustment has no protocol for finding.
The Body's Biomechanical Shift: Pelvis, Ligaments, and Load
Every foundation problem eventually shows up in the structure it supports. And pregnancy changes that structure fast.
Navigating pregnancy comes with a host of physical changes, many of which center on the pelvis and lower back. The sacrum shifts. The supporting ligaments stretch under new mechanical demand, and the muscles around the pelvis adapt to a load they were not built to carry a year earlier.
None of this is incidental discomfort. It is the mechanical backdrop that decides whether an adjustment is even asking the right question.
| Structure | Change During Pregnancy | Mechanical Consequence |
|---|---|---|
| Sacrum and Pelvic Joints | Shifts to accommodate the growing uterus and prepare for delivery | Uneven weight distribution can concentrate mechanical stress in one side of the pelvis rather than transmitting it evenly |
| Round and Supporting Ligaments | Stretches and lengthens to support the expanding uterus, particularly through the second trimester | Tension in the stretched ligament can create sharp or pulling pain and contribute to restricted space within the pelvis |
| Surrounding Musculature | Adapts to a new mechanical load it was not previously carrying | Compensatory muscle tension can mask an underlying joint restriction that a generic adjustment never isolates |
| Maternal Pelvis (Structural Capacity) | Bears increasing mechanical demand as gestation progresses | A pelvis already constrained in size or alignment is recognized as a factor capable of limiting fetal space during later gestation |
How Round Ligament Tension Shows Up as Pain
The round ligaments narrow that broad anatomical picture down to one specific structure patients feel directly. These ligaments increase in diameter and length as pregnancy progresses.
That growth is not incidental. In the second trimester, the round ligaments may cause cramping and pain as they stretch and contract, a pattern documented in maternal anatomy research from the National Center for Biotechnology Information.
At times, this pain is sharp. It can pull rather than ache, which is exactly why patients mistake it for something more serious than a stretching ligament under new mechanical load.
How Uterine Constraint Can Influence Fetal Positioning

The pelvis is not the only structure carrying mechanical stress during pregnancy. The uterus has its own limits on how much room it can offer a growing baby.
Intrauterine constraint is what happens when those limits get reached early. Space narrows before the baby has finished the positioning that late gestation normally allows.
A misaligned pelvis is one thing that drives that narrowing. So is ligament tension that pulls the uterus into a lopsided shape instead of a balanced one.
None of this means an adjustment repositions a fetus directly. The Webster Technique corrects the structural imbalance that can concentrate constraint in the first place, and any shift in position follows from that correction rather than from a maneuver aimed at the baby.
What 'Constraint' Means Mechanically
Mechanically, constraint means the uterine environment is being shaped by outside forces rather than by fetal growth alone. A pelvis transmitting load unevenly can press the uterus into a form that limits movement.
Adult chiropractic protocols were never built to isolate this. Pediatric and prenatal chiropractic technique operates on a different structural logic than adult adjustment, evaluating growth, ligament laxity, and fetal space as their own category of mechanical problem.
What Happens When Generic Protocol Meets a Non-Generic Case
A standardized care plan assumes every pregnant patient runs the same mechanical timeline. That assumption breaks the moment two patients walk in with different structural pictures.
A patient at twelve weeks with mild round ligament discomfort is not managing the same foundation as one at thirty-six weeks with a breech presentation and chronic sciatica. One pelvis is just beginning to shift under new load. The other has been compensating for months, and the constraint has had time to compound.
Fixed-visit protocols exist to make scheduling predictable. They do not exist to match care to what a specific pelvis is actually doing. A ten-visit plan built for operational efficiency treats both patients as one, and the mechanical reality underneath each case never gets that same courtesy.
What the Research Record Actually Shows

The safety question deserves a straight answer, not a hedge. A systematic review of adjustment research found limited evidence of adverse events in pregnant and postpartum populations.
That same review documented one case report of a serious adverse event in the cervical spine. Alongside it sat a small number of minor and short-lived adverse events in the low back. Findings like these are cataloged in the research archived through PubMed Central, the repository that indexes this literature for clinicians.
Serious injury reads as rare in the record, not absent. And that distinction is exactly why certification is not optional. Webster Certification is the minimum standard for treating pregnant patients, because an uncertified adjustment is analyzing the wrong structure entirely.
| Adverse Event Type | Region Affected | Reported Frequency |
|---|---|---|
| Serious adverse event | Cervical spine | Reported as a single case in the systematic review, indicating extreme rarity |
| Minor adverse event | Low back | Described as a small number of short-lived, transient reactions following adjustment |
| Serious adverse event | Sacral or pelvic region | Not identified in the reviewed literature on pregnant and postpartum populations |
| Minor adverse event | Cervical spine | Not documented as a distinct pattern separate from the single serious case noted above |
What Webster Certification Actually Requires
Certification is not a credential a chiropractor adds to a resume for marketing purposes. It is the actual training that teaches a practitioner what the pelvic foundation looks like when it is carrying pregnancy load unevenly.
And that training does not come bundled with a chiropractic license. The license certifies general adjustment competency. It says nothing about whether a doctor can isolate a sacral misalignment or a ligament pattern specific to a shifting pelvis.
Without this training, an adjustment is not analyzing the wrong problem carefully. It is not analyzing the pregnancy-specific problem at all.
The Credentialing Pathway Through the ICPA
The International Chiropractic Pediatric Association administers the credentialing pathway this protocol requires. A practitioner works through coursework built around the exact assessment this technique uses, not general adjustment principles applied loosely to a pregnant patient.
That pathway covers the sacral and ligamentous analysis this article has already laid out. It is built around the same load-bearing pelvis this section keeps returning to, never a generic spine assumed to behave the same whether or not it is pregnant.
How a Certified Assessment Is Actually Structured
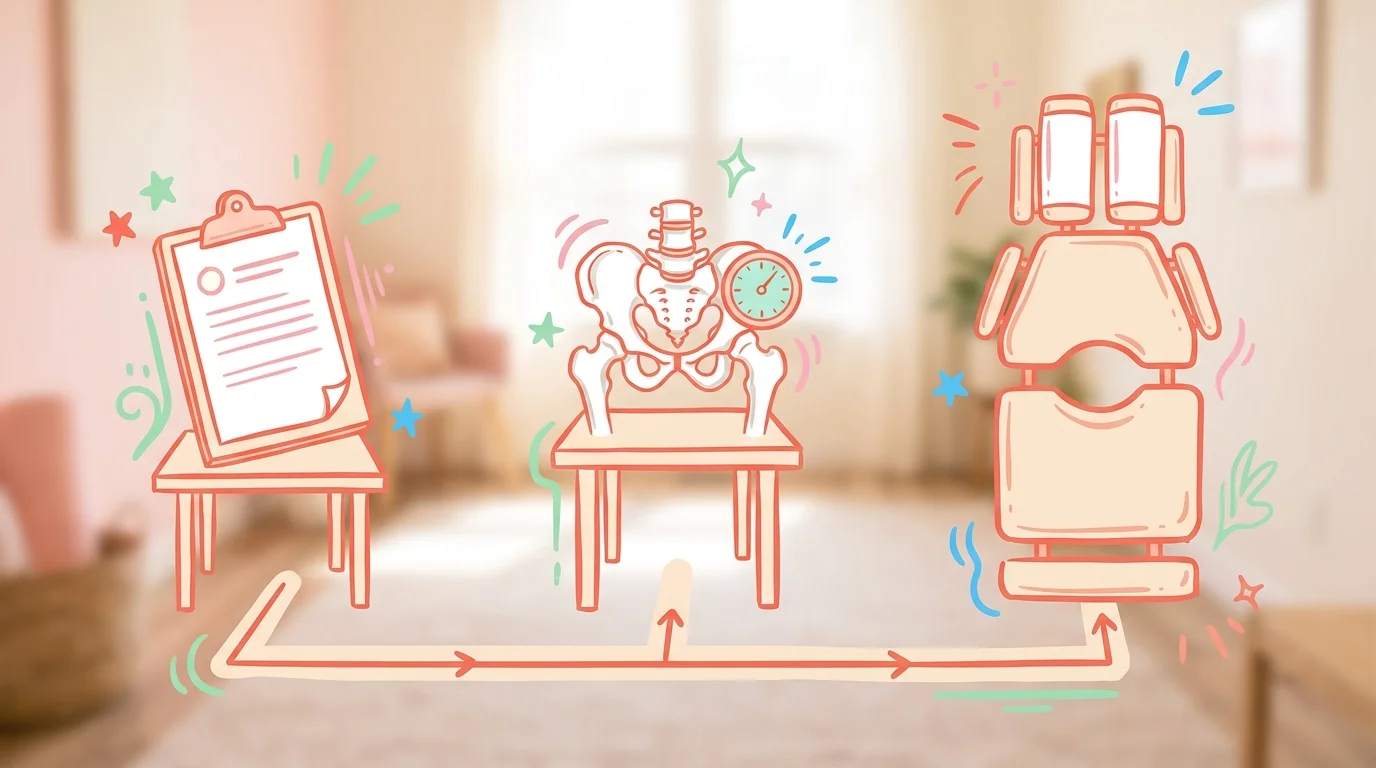
A certified assessment does not open with the adjustment. It opens with a structural question. Is the load-bearing foundation of the pelvis carrying pregnancy weight evenly, or is it piling stress onto one side?
That one question decides everything that comes after it. And it is exactly the question a general adjustment never bothers to ask.
Webster Certified analysis treats the assessment as its own separate phase, kept apart from the adjustment. The two are sequenced, never blended, because what the first one finds decides what the second one corrects.
| Assessment Stage | What Is Evaluated | Clinical Purpose |
|---|---|---|
| Structural History Review | How the pregnancy has progressed, where discomfort concentrates, and whether round ligament tension or sacral symptoms have already appeared | Establishes the baseline picture of the pelvic foundation before any hands-on work begins |
| Sacral Position Analysis | A specific palpatory and postural evaluation of where the sacrum sits relative to the pelvis under current pregnancy load | Identifies the exact misalignment pattern rather than assuming a generic restriction |
| Ligament and Soft Tissue Evaluation | Whether surrounding muscle work is compensating for an imbalance or supporting a genuinely balanced structure | Confirms whether tension around the pelvis reflects the sacral finding or a separate compensating pattern |
| Targeted Adjustment | The specific sacral misalignment identified during analysis, corrected as a distinct step rather than blended into the assessment | Directs the adjustment at the actual imbalance found that session, not a fixed routine repeated regardless of findings |
The Assessment Sequence, Step by Step
The sequence starts with a structural history. A practitioner reviews how the pregnancy has moved along, where discomfort concentrates, and whether round ligament tension or sacral symptoms have already shown up.
Next comes the sacral analysis itself. This is a specific palpatory and postural evaluation of sacral position, checking how the sacrum sits relative to the pelvis under current pregnancy load.
Ligament and soft tissue findings get read alongside the sacrum. Muscle work around the pelvis and lower back shows whether the surrounding tissue is compensating for an imbalance or genuinely supporting a balanced structure.
What Distinguishes the Adjustment Itself
The adjustment comes only after that analysis is finished. It targets the exact sacral misalignment the assessment found, not a generic restriction chosen because it happened to read as tight that day.
Care built this way looks nothing like a fixed-visit plan stamped across every patient. Each session opens with that same structural question, and the adjustment shifts as the answer shifts across the pregnancy.
Frequently Asked Questions
The mechanics explain most of it. But a few plain questions still deserve plain answers.
What is the primary goal of the Webster Technique?
The goal is pelvic balance, not fetal positioning. A Webster Certified assessment corrects sacral misalignment so the pelvis carries pregnancy load evenly, and any change in fetal position follows from that correction rather than from a maneuver aimed at the baby.
Is the Webster Technique safe throughout all trimesters of pregnancy?
The evidence supports adjustment care across every trimester when a certified practitioner delivers it. Prior review found adverse events after spinal adjustment to be uncommon in pregnant and postpartum patients. That reads as reassurance, not a warning.
How does the Webster Technique differ from a standard chiropractic adjustment?
A standard adjustment addresses whatever joint restriction shows up that day. A Webster Certified analysis reads sacral position, ligament tension, and pregnancy-specific structural change first. Only then does it adjust, based on what those findings actually say.
Does the Webster Technique turn breech babies?
No. The Webster Technique does not turn a baby directly. It corrects pelvic imbalance and eases intrauterine constraint, and any repositioning follows from that structural correction rather than a hands-on move on the fetus.
How often should Webster Technique adjustments occur during pregnancy?
Frequency follows the structural picture, never a fixed calendar. A pelvis compensating for months is not the same mechanical reality as one just beginning to shift. So care adjusts to what the assessment finds at each visit.
What does a Webster Technique certification mean for a chiropractor?
It means training that goes beyond a general chiropractic license. The International Chiropractic Pediatric Association credentials practitioners specifically in the sacral and ligamentous assessment pregnancy demands. A standard license does not cover that.
What anatomical structures does the Webster Technique assessment evaluate?
The assessment reads sacral position relative to the pelvis, ligament tension including the round ligaments, and how the surrounding soft tissue is compensating. Each one shows whether the pelvic foundation is carrying pregnancy load evenly or piling it onto one side.
The Bottom Line
The pelvis is a load-bearing foundation. Under pregnancy load, it either spreads that stress evenly or piles it into one place as pain and constraint. That truth holds no matter who is doing the adjusting.
A general adjustment finds whatever reads as restricted that day. A certified analysis finds where the foundation itself is compensating, and corrects that instead. Webster Certified care is built for the second question, and the first one was never enough.
That is the standard pregnancy load demands, and it stops being optional the moment that load enters the picture. So if the pelvis is carrying it unevenly, the right next step is a structural assessment built for exactly that — schedule a prenatal appointment at Momma's Chiro.